Medical Rx and Infusions: The Overlooked Side of High-Cost Rx

Medical Rx and Infusions: The Overlooked Side of High-Cost Rx

Medical Rx and Infusions: The Overlooked Side of High-Cost Rx

As plans build their high-cost Rx strategy for 2027, the drugs paid under the medical benefit are often the part left out. They shouldn’t be.

By Jake Velie, CPT | Founder, Chairman & CEO, National Integrative Health

Most conversations about high-cost drugs start with the pharmacy benefit, and for good reason. Specialty medications make up only about 2% of pharmacy volume but roughly 55% of pharmacy spending, according to the UnitedHealthcare 2026 Health Trends Report.

But a large share of high-cost drug spend never touches the pharmacy benefit at all. Infusions and injectables given in hospital outpatient departments, infusion centers and physician offices are billed on medical claims, usually under J-codes. When drugs paid through the medical benefit are included, WTW estimates that pharmacy accounts for approximately 36% of total healthcare claims, with pharmacy costs expected to rise 11.5% in 2026.

For plans building a 2027 strategy, that matters. A strategy that manages only pharmacy claims is managing only part of the problem.

Why Medical Rx Gets Missed

Medical-benefit drugs are easy to overlook for structural reasons:

  • They’re billed like procedures. The drug cost is often bundled with administration and facility charges, which makes it harder to see what the drug itself costs.
  • They sit outside the PBM’s view. Pharmacy benefit managers typically see pharmacy claims, not infusions billed through the medical plan.
  • They’re reviewed by different people. Medical claims and pharmacy claims are often managed by separate teams, vendors, and reports.
  • They show up late. By the time a large infusion claim reaches stop-loss reporting, the cost decisions have already been made.

The result is a blind spot in exactly the place where costs are growing. UnitedHealthcare reports that the cost of claims over $100,000 rose 12.9% from 2024 to 2025 across its self-funded and fully insured books (UnitedHealthcare).

Site-of-Care: Where the Opportunity Is Largest

Where an infusion is given can change its cost dramatically. Hospital outpatient departments remain the highest-cost setting, while home and ambulatory infusion consistently cost less, according to Optum. Optum cites a 2026 matched cohort study in the Journal of Managed Care & Specialty Pharmacy, which found similar clinical outcomes in alternate sites of care, with total cost of care approximately 33% lower.

The differences show up at the drug level, too. A review of commercial claims for immunoglobulin therapy found the cost per infusion was 31% lower at home than in the outpatient setting, $3,293 compared with $4,745 (AJMC).

Site-of-care is a clinical decision first. Not every patient or therapy is right for an alternate setting, and changes should be coordinated with treating providers. But in my experience, many plans have never looked at where their infusions are happening, let alone whether a lower-cost setting would be appropriate.

Moving patients is only part of a site-of-care strategy, though. Some patients need to stay in the hospital outpatient setting, at least for a time, and they are often the most complex and most expensive cases. At National Integrative Health, our Managed Care business manages infusions, injectables and oral therapies. When care has to stay in the hospital outpatient setting, we oversee the treatment and medication ordering and negotiate the cost of treatment until care can be moved to a more appropriate setting.

The results of any infusion strategy depend on how many treatments it can actually reach. Drawing on NIH’s plan design expertise and in-house managed care networks, we can manage 100% of a plan’s infusions, in every care setting. Most non-integrated vendors manage only a portion, which leaves the most critical cases, often the ones that must stay in the hospital, unmanaged.

What a Medical Rx Review Looks Like

Beyond site-of-care, a review of medical-benefit drug claims should check a few basics:

  • Billed units match the dose actually administered
  • Drug pricing is reasonable compared with available benchmarks
  • The same therapy isn’t being paid under both the medical and pharmacy benefits
  • Biosimilars or clinically equivalent alternatives have been considered where appropriate

Five Steps for 2027

For plans preparing for the 2027 plan year, here is a practical starting point:

  1. Pull 12 months of medical claims with J-codes and rank the drugs by total spend.
  2. Map where each therapy is administered: hospital outpatient, physician office, infusion center or home.
  3. Identify site-of-care opportunities and review them with treating providers. For therapies that must stay in the hospital, make sure ordering and treatment costs are still managed.
  4. Review billing and pricing on the highest-cost claims.
  5. Bring stop-loss into the conversation early, so the carrier understands how medical Rx is being managed before renewal.

The Bottom Line

A durable high-cost Rx strategy brings pharmacy, medical and PBM spend into one view. Infusions and other medical-benefit drugs are often where the largest single claims sit, and where the most practical opportunities are. The strongest strategies reach every infusion in every setting, including the cases that have to stay in the hospital. Plans that build that into their 2027 planning will be working from the full picture, not just part of it.

About the Author

Jake Velie, CPT, is Founder, Chairman & CEO of National Integrative Health, an integrated pharmacy program for high-cost medications that serves plan fiduciaries with full transparency. He writes regularly on high-cost drug management for benefits professionals. The NIH team will be at the 19th Annual HVBA Conference at the Logan Inn in New Hope on November 19.

Sources

UnitedHealthcare, A prescription for easing the pain of pharmacy care costs: https://www.uhc.com/employer/news-strategies/prioritizing-pharmacy-care-costs

WTW 2026 Best Practices in Healthcare Survey (via Morningstar/GlobeNewswire): https://www.morningstar.com/news/globe-newswire/9855110/wtw-2026-best-practices-in-healthcare-survey-us-employer-healthcare-costs-set-to-rise-at-fastest-pace-in-more-than-two-decades

UnitedHealthcare 2026 Health Trends Report: https://www.uhc.com/agents-brokers/employer-sponsored-plans/news-strategies/annual-health-trends-report

Optum, Why site of care strategy matters in infusion therapy: https://business.optum.com/en/insights/site-of-care-strategy-infusion-therapy.html

AJMC, Managing Cost of Care and Healthcare Utilization in Patients Using Immunoglobulin Agents: https://www.ajmc.com/view/managing-cost-of-care-and-healthcare-utilization-in-patients-using-immunoglobulin-agents

Stop-Loss and Actuarial Partnerships: Why Underwritable Rx Strategy Wins

By Jake Velie, CPT
Founder, Chairman & CEO, National Integrative Health

Publication date: October 29, 2026

Every self-funded renewal comes down to one question from the stop-loss underwriter: how much of next year’s risk can be seen, measured, and priced? When high-cost drug spend is unmanaged, the honest answer is “not much.” The carrier then protects itself the only way it can, with higher specific rates, higher deductibles, lasers, or exclusions.

This article looks at that problem from the underwriter’s side of the table, and explains how National Integrative Health (NIH) works with stop-loss carriers and actuarial partners to make high-cost Rx risk something they can price.

The problem underwriters are pricing

High-cost claims are no longer rare events for a self-funded plan. Sun Life reports that million-dollar-plus claims are up 46% since 2022.¹ Its prior analysis found that 88% of employers experienced at least one stop-loss claim in a given benefit year between 2020 and 2023.² Tokio Marine HCC reports that claims exceeding specific deductibles by at least $2 million rose 213% between policy years 2020 and 2025, and expects a tightening rate environment through at least 2027.³

Drugs are a major part of that tail. In the 2025 IFEBP medical stop-loss premium survey, specialty pharmacy was cited in 47% of catastrophic claims, and 49% of plans reported claims above $1 million, up from 23% the year before.⁴ Sun Life identified Keytruda as the highest-cost drug in its book, with $84.4 million in spend.⁵ Cell and gene therapies add a different kind of risk: claims remain infrequent, but a single treatment can exceed $2 million to $3 million.⁴ ⁶

The result is visible at renewal. Single-year stop-loss increases ran roughly 8.8% to 10% in 2025.⁴ Amwins’ Stealth reports that 29% of its groups had at least one lasered individual in 2025.⁷ Lockton notes that clients increased deductibles at nearly twice the 2024 rate to manage premium.⁸

Why unmanaged Rx is hard to underwrite

From a clinical and actuarial standpoint, four features make high-cost drug spend difficult to price.

1. Variability in unit cost. The same infused drug can be billed at very different rates depending on where it is given. A hospital outpatient department, a physician office, an ambulatory infusion center, and the home can each produce a different allowed amount for the same J-code and dose. If site of care is not managed, the underwriter must assume the most expensive setting.

2. Split visibility between medical and pharmacy. Specialty drugs move between the pharmacy benefit and the medical benefit. When those claims are administered separately, no single party sees the full drug picture for a member. Underwriters receive partial data and price the gap.

3. Forward risk that history does not show. New therapies enter the market quickly and do not appear in prior claims experience. Lockton points out that past claims experience may not reflect the impact of future catastrophic cases, which pushes carriers toward forward-looking assumptions.⁸ A carrier that cannot see how a plan will handle a new high-cost therapy will load for it.

4. Waste built into the medication order. Many infused drugs are dosed by weight or body surface area and supplied in single-dose vials. When an order uses the wrong combination of vial sizes, the plan pays for drug that is opened and then discarded. A 2016 study in The BMJ estimated that payers spend about $1.8 billion a year on discarded amounts of the top 20 cancer drugs sold in single-dose vials alone.⁹ Medicare billing guidance already expects billed units to match the smallest combination of vials that delivers the prescribed dose.¹⁰ If no one audits the order, the underwriter has to assume that waste is part of the cost.

Each of these features adds uncertainty. Uncertainty becomes margin in the renewal quote.

What “underwritable” means

An underwritable Rx strategy is one that a carrier and its actuaries can model with confidence. In practice, that requires:

  • Defined clinical pathways. Prior authorization, dose verification, an audit of the vial combination on each order, and appropriateness review based on published clinical criteria, applied the same way every time.
  • Managed site of care. A documented process for moving clinically eligible patients to lower-cost, clinically appropriate settings.
  • Consistent acquisition cost. Drug pricing tied to transparent, predictable benchmarks rather than facility chargemaster rates.
  • Integrated claim data. Pharmacy and medical drug claims reviewed together, so the carrier sees one view of each high-cost member.
  • Early notice of large claimants. Identification of high-cost members as soon as therapy is started, not after the claim has crossed the specific deductible.
  • A repeatable record. The same results year over year, so the actuary can give credibility to the plan’s own experience.

When these elements are in place, the underwriter has fewer unknowns. Fewer unknowns support more stable pricing, fewer lasers, and better access to terms such as no-new-laser and rate caps.

How NIH works with carriers and actuaries

NIH operates an integrated fiduciary pharmacy program for high-cost medications. Our work with stop-loss carriers and actuarial partners follows the same six principles listed above.

Clinical pathways, applied by pharmacists. Our clinical team reviews high-cost therapies for appropriateness, dose, and duration before and during treatment, using published clinical criteria. The same review is applied every time, which gives the carrier a known control at the point where cost is decided.

Our pharmacists also audit each medication order against the prescribed dose. Orders are often written with a combination of vials that does not account for waste. When that happens, we change the order to match the treatment more precisely. The patient receives the same drug at the same dose, and the treatment does not change in any way. The only difference is that the plan stops paying for drug that is thrown away. In many cases, this step alone saves the plan significant money.

Site-of-care management. We coordinate with prescribers and patients to place infusions in the safest, most cost-effective setting the patient’s condition allows. Each move is documented. Patient safety and continuity of care come first.

Predictable acquisition cost. We source high-cost medications at the lowest available net cost, with pricing tied to transparent benchmarks rather than facility chargemaster rates. For individual high-cost members, NIH can arrange single-case agreements. For groups, enterprise agreements set predictable terms across the population. Both give the underwriter a defined cost for risk that would otherwise be open-ended.

Medical and pharmacy integration. We look at medical-side drug claims, including infusions, injectables, biosimilars, and J- and Q-code billing, together with pharmacy claims. Carriers and actuaries receive one consistent picture of each member’s drug therapy.

Early notice of large claimants. Because we review high-cost therapies at the start of treatment, we can identify large claimants before they reach the specific deductible. We share that information with the carrier and provide drug-level detail in a format actuaries can apply to their models.

A record the actuary can credit. We apply the same clinical, site-of-care, and pricing controls year over year and report the results consistently. We work with the broker, TPA, carrier, and actuary ahead of each renewal window, so the plan’s own experience can carry more weight in pricing. Our goal is to answer the underwriter’s questions before renewal, not during it.

What this means for brokers, TPAs, and employers

For mid-market groups, often in the 500 to 1,000-life range, one high-cost member can change the renewal. These groups have the least room to absorb a laser or a large rate increase.

Three practical steps help:

  1. Start before the renewal. Identify current and expected high-cost drug members 120 to 180 days before renewal.
  2. Put the controls in writing. Carriers price what they can document. Clinical criteria, site-of-care rules, and pricing terms should be written and shared.
  3. Bring the carrier in early. Share the Rx strategy with the stop-loss underwriter as part of the submission, not as an appeal after the quote arrives.

Conclusion

Stop-loss carriers are not opposed to high-cost drug risk. They are opposed to risk they cannot measure. Plans that manage high-cost Rx with clear clinical controls, integrated data, and predictable pricing give underwriters and actuaries what they need to price fairly.

That is the work NIH does. If your group is approaching renewal with high-cost drug exposure, we can review the risk with you, your broker, and your carrier before the quote is set.

Footnotes

  1. Sun Life, “2026 High-Cost Claims and Injectable Drug Trends Report.” https://view.ceros.com/sun-life/high-cost-claims-and-injectable-drugs-report
  2. Risk & Insurance, “Million-Dollar Medical Claims Soar, Putting Employers Under Pressure.” https://riskandinsurance.com/million-dollar-medical-claims-soar-putting-employers-under-pressure/
  3. Risk & Insurance, “Medical Stop Loss Claims Above $2 Million Have Tripled Since 2020” (Tokio Marine HCC – A&H 2026 Annual Market Report). https://riskandinsurance.com/medical-stop-loss-claims-above-2-million-have-tripled-since-2020/
  4. International Foundation of Employee Benefit Plans, “2025 Medical Stop-Loss Premium Survey for Self-Funded Plans.” https://blog.ifebp.org/2025-medical-stop-loss-premium-survey-for-self-funded-plans/
  5. Sun Life / SLC Management, “Cancer still tops high-cost health claims but muscle and orthopedic conditions are making surprise surge.” https://www.slcmanagement.com/us/en/newsroom/news-releases/announcement/cancer-still-tops-high-cost-health-claims-but-muscle-and-orthopedic-conditions-are-making-surprise-surge-sun-life-report/123968/
  6. Midwest Business Group on Health, “SpecialtyRx Toolkit: Financial Impact and Cost Management of Cell and Gene Therapies.” https://mbgh.org/specialtyrxtoolkit/cgt/cost-mgt
  7. Amwins / Stealth Partner Group, “Stop Loss State of the Market Report 2025.” https://www.amwins.com/docs/default-source/external-linked-documents/stealth-docs/stealth_sotm_2025.pdf?sfvrsn=8eb1bdc2_2
  8. Lockton, “Medical Stop Loss – People Solutions Market Update, Q3 2025.” https://insights.lockton.com/people-solutions-market-update/q3-2025/medical-stop-loss
  9. Bach PB, Conti RM, Muller RJ, Schnorr GC, Saltz LB. “Overspending driven by oversized single dose vials of cancer drugs.” BMJ 2016;352:i788. https://www.bmj.com/content/352/bmj.i788
  10. Noridian Healthcare Solutions (Medicare Administrative Contractor), “Drug Wastage – JW and JZ Modifiers.” https://med.noridianmedicare.com/web/jfb/topics/drugs-biologicals-injections/drug-wastage-jw-and-jz-modifiers
  11. Centers for Medicare & Medicaid Services, “Discarded Drugs and Biologicals – JW Modifier and JZ Modifier Policy FAQs.” https://www.cms.gov/medicare/medicare-fee-for-service-payment/hospitaloutpatientpps/downloads/jw-modifier-faqs.pdf
  12. Self-Insurance Institute of America, “High-Cost Drug Market Update” (2025 High-Cost Drug Forum). https://www.siia.org/files/2025/High-Cost Drug Forum/2)__High-Cost_Drug_Market_Update.pdf

How to Build a Stable High-Cost Rx Strategy for 2027 and Beyond

Stability, integration, and predictability matter. A durable strategy connects pharmacy and medical claims, clinical review, sourcing, and stop-loss planning. 

By Jake Velie, CPT | Founder, Chairman & CEO, National Integrative Health 

Over the past few weeks, brokers, TPAs, and plan sponsors have asked me the same question: will the strategy we rely on today still be there next year? 

That is a fair question. When savings depend on one contract or channel, a change can put expected savings and member continuity at risk. A durable strategy connects pharmacy and medical claims, clinical review, sourcing, infusion setting, and stop-loss support. 

Why Stability Matters 

High-cost specialty drugs and infusions can drive significant plan spend. The risk is not only what a claim costs today. If a sourcing path or contract changes, members may face delays or cost changes, and the plan may need to revisit its savings and renewal assumptions. 

Carriers and actuaries need clear assumptions they can review. If savings cannot be measured, documented, and explained, they are hard to rely on when planning for renewal. 

How to Build a More Durable Strategy 

Avoiding variability does not mean giving up savings. It means building a foundation that can be measured and reviewed. 

Use more than one path. Review clinical needs, claims data, sourcing options, and the infusion setting. Choose the approach that fits the medication and the member. 

Put the terms in writing. Agree on what counts as savings, which costs and fees are included, and how results will be measured and validated. 

Ask the hard question. If market conditions change, what happens to the member, the claim, and the expected savings? 

Five Steps to a Long-Term High-Cost Rx Strategy 

1. Review the whole plan. Look at pharmacy claims, medical drug claims, and PBM terms together. Separate reviews can miss overlap and leave gaps. 

2. Manage medical and pharmacy together. Include infusion and J-code claims. When clinically appropriate, compare the infusion setting and total cost before changing where care is delivered. The clinical decision comes first. 

3. Coordinate with stop-loss early. Share the strategy before renewal and ask how the carrier will consider it in underwriting. Do not assume a program will lower rates. Put the assumptions and measures in writing. 

4. Use the agreement that fits the claim. A single-case agreement addresses a specific claim; an enterprise agreement sets terms across a plan. Choose the structure that fits the needs, document scope, pricing, and responsibilities. 

5. Build around validated results. Set the baseline, measurement period, and savings method up front. Give the plan, carrier, and actuary results they can review. 

What We Do at NIH 

National Integrative Health works alongside a plan’s existing PBM, TPA, and health plan. We review high-cost pharmacy and medical-benefit claims, including infusions, then look for the right path claim by claim. ¹ 

Depending on the medication, eligibility, and clinical fit, options may include direct manufacturer contracting, 340B sourcing, biosimilars or therapeutic alternatives, patient or manufacturer assistance, a different infusion setting, clinical trials, or a combination of pathways. Clinical review and coordination with members and treating providers come first. 

We coordinate with stop-loss carriers so they can evaluate the approach in underwriting. Savings are measured against actual plan-paid cost, net of fees and rebates.  There are no implementation fees, per-employee-per-month (PEPM) fees, or per-member-per-month (PMPM) charges. Fees are cost-plus and fully transparent, invoiced only after savings are delivered.  ² 

One 550-Life Group, 12 Months In 

A 550-life group came to NIH through a TPA partner that had previously been covered only through a BUCA carrier. Prior to the effective date, NIH worked with the stop-loss carrier to reduce the group’s premium by 10% because NIH’s program savings were actuarially validated up-front. After 12 months, reported drug cost moved from $120 to $85 per member per month, a 29% decrease. The $85 PMPM included all NIH fees. ³ 

10% Stop-loss premium reduction reported before launch $120 → $85 Reported drug cost PMPM after 12 months, including NIH fees, 29% lower 

These results reflect one group’s plan and contract terms. They are not a guarantee of results for another plan. 

Where to Start 

Start with real claims data. A repricing analysis can show where lower-cost options may be available and how potential savings can be measured. Reach out to see if your plan qualifies for a free Repricing Analysis. 

Request a Repricing Analysis 

About NIH 

National Integrative Health works alongside health plans, TPAs, and PBMs to manage high-cost pharmacy and infusion claims through data review, clinical coordination, sourcing, infusion care, stop-loss support, and clinical trials. Learn more at NationalIntegrativeHealth.com. 

Footnotes 

1. Program description. NIH’s 2026 company brochure describes work across pharmacy and infusion claims, clinical review, sourcing, site-of-care evaluation, and actuarial/underwriting support. This is NIH marketing collateral, not independent validation. NIH – Company Brochure 2026 

2. Fee model. NIH’s 2026 overview states there are no implementation fees or PEPM/PMPM charges, and that payment is tied to delivered savings. Confirm the exact contractual wording for the engagement being described. NIH – Quick Overview 2026 

3. The group had only been with a BUCA before NIH, the carrier reduced premium by 10% before launching because it could underwrite the program, and the $85 PMPM included NIH fees.  

Three Dragons, One Network

What Stacey Richter and Evan Anderson got right about carrier networks, and what employers can do now to cut costs

By Jake Velie, Founder, Chairman & CEO, National Integrative Health

I have spent 13 years on the health plan side of this business. I have watched employers pay more each year for the same care while our industry explains it away. So when Stacey Richter sat down with Evan Anderson on Relentless Health Value1, I found myself nodding along.2

Stacey called the status quo carrier network a “three-headed monster.” I see three dragons: the discount illusion, unchecked claims, and price variation by site of care. Each guards a different part of employer spending.

Here is what I have seen on the ground, and how employers can challenge each one.

The bottom line for executives

  • A discount is not proof of savings. One study found cash prices below insurers’ median negotiated rates in 47% of its comparisons.6
  • Many plans do not routinely compare high-cost bills with their contract terms. Errors can go undetected unless someone checks.
  • Where care happens can matter as much as what care happens. The same drug can cost many times more depending on the building.
  • High-cost claims may affect stop-loss costs when they reach the policy’s specific attachment point, subject to the contract and underwriting.

None of this requires blowing up your plan. It requires better questions and better data.

Start with the right question

Stacey opened with a question nobody asks anymore: what is a network? She pointed to Katy Talento’s essay on a post-network world3, which describes a network, at its simplest, as a set of contracts between carriers and providers. Evan said plans need a way to confirm those contracts are honored.

Evan described a gap between how networks are presented and how their contracts work. Mark Cuban has also called for standardized contracts.4 Stacey warned that layered contracts can bury terms and incentives that work against the plan sponsor.

Stacey’s point that marketing claims are not a substitute for data belongs in every benefits committee discussion. I learned it early. On the pharmacy side, a self-funded plan can usually see what it paid for a medicine. On the medical side, as I told Stacey on her show5, the whole story can get “embodied in a J-code and a Q-code.” You see a code and a dollar amount. You may not see what the drug cost, who bought it, or why it was given at that site. If you cannot see it, you cannot manage it.

Dragon one: the discount illusion

Evan argued that network discounts can mislead employers when they are calculated against hospital list prices with little connection to a defensible market price.

The research backs him up. A 2023 Health Affairs study by Johns Hopkins researchers6 examined 70 common services across 2,379 hospitals. Cash prices were below median insurer-negotiated prices in 47% of the study’s comparisons. Stacey explained why this can persist: when an intermediary is paid as a percentage of spend, higher costs can mean more revenue.

I agree with both of them, and I would make it even simpler for executives. When a vendor tells you they saved you 60%, ask one question: 60% off of what? If nobody can answer that in plain English, you do not have a savings number. You have a marketing number. The only number that matters is what you actually paid compared with what you should have paid.

Dragon two: the unchecked claim

The second head is payment integrity. Evan described claims systems built on legacy platforms, with contract logic layered over time. His point was that the plan often lacks a practical way to independently check the result.

Stacey pointed to her conversation with Kimberly Carleson7, where Carleson cited estimates that as many as 80% of hospital bills may contain an error. Treat that as an estimate discussed in the episode, not a universal audited rate. Evan pointed to Stacey’s episode with Andrew Tsang8 on revenue cycle management, described there as a $200 billion industry. When billing and payment disputes are not resolved, patients, independent practices, and employers can end up carrying the burden.

This is an area executives can address, but the law is specific. The Consolidated Appropriations Act of 20219 bars gag clauses that prevent plans and issuers from accessing provider-specific cost or quality information and de-identified claims data, subject to applicable privacy protections. That does not guarantee every plan automatically receives a complete, usable claims file. Plan sponsors still need to confirm their contract terms, data feeds, and safeguards. Ask what data is available, how it is delivered, and who reviews high-cost claims before payment.

Dragon three: the wrong chair

This is the dragon I deal with every day.

Stacey referenced Jim Jusko’s argument10 that the same physician delivering the same service may be paid different rates under different network contracts. She described that as a dysfunctional market. Evan pointed to substantial price gaps between hospital-based and outpatient care. They discussed an example from Stacey’s episode with Ivana Krajcinovic11: the independent practice charged $135 for a chemotherapy infusion, while a hospital down the street charged $13,560 for the same infusion, according to the episode. The episode underscored that the same treatment may carry very different prices under different provider contracts. Stacey noted that both providers were described as in-network.

That episode also described a member’s hospital bill of $90,000 for a series of infusions, compared with an alternative-site estimate of $185 all-in. In another example, two members could have saved a combined $1 million by receiving the same infusions at a different site. These are examples reported in the episode; the amounts should be understood in the context and scope described there.

In September 2026, the Employee Benefit Research Institute12 reported an analysis of 106 physician-administered outpatient drugs using commercial claims from 2023–2024. Hospital outpatient departments were paid more than physician offices for 93 of the 106 drugs; per-unit prices were 102% higher on average and 64% higher at the median. The study covers physician-administered drugs, not only infusions. A separate 2026 study of more than 52,000 matched infusions reported hospital outpatient costs about 42% higher than alternative sites, with similar outcomes.13 Those study averages do not mean every patient can move; site-of-care decisions require clinical review. MedPAC has also warned that paying hospitals more for the same service can steer care toward the highest-paid setting.14

Stacey and Evan are right about site of care, and I would add one thing. Site of care is not only about moving the patient. In one case I worked on, we estimated that a plan was paying roughly $80,000 more per dose of Ultomiris than necessary. We did not move the patient. We changed how the drug was purchased and how the contract was structured. Same medicine, same chair, same building, different contract. Sometimes the answer is a different setting. Sometimes it is a better price where the patient already receives care. Either way, a cost is not fixed just because it showed up on a claim.

The cost that can follow you to renewal

This is the piece I would add to Stacey and Evan’s list, and it is the one I care most about. When Keith Hartman and I joined Stacey for episode 5305, our message was simple: overpaying for infusions can affect stop-loss costs.

An eligible claim that crosses a plan’s specific attachment point can affect reimbursable losses and may factor into renewal pricing, depending on policy terms, experience, and underwriting. Sun Life’s 2026 analysis15 reported a 46% increase in million-dollar-plus claims over the four-year period it studied, with specialty drugs among the key drivers.

I am also seeing stop-loss carriers take a more active role in cost containment. When risk carriers start managing claims themselves, it shows how much attention this issue is getting.

Ahead of the October 1, 2026 renewal, a broker overseeing more than 70 self-funded groups asked whether an infusion carve-out could be in place after reviewing Keytruda and other high-cost drug claims. That is a broker doing the math.

Why the dragons persist

Stacey asked whether employers could simply get rid of networks. She and Evan emphasized the disruption that could cause and the continued need for access and repricing. Stacey also cited Dr. Eric Bricker’s point that operating without a network is difficult because networks do the repricing. Without that reference point, plans may not know what a service should cost.

Evan’s point: cutting one head does not solve the underlying opacity and misaligned incentives. Those problems can persist across network arrangements.

I agree that walking away from a network is not the answer for most employers. Members need access, and disruption is real. But being stuck with networks does not mean being stuck with network prices. Employers can challenge all three dragons with better data and oversight.

Four ways to fight back

Stacey asked what a workable solution looks like. Evan outlined four paths. Here is how I would approach each one.

Switch networks, but only with your own data. Evan is right that you need real prices and your own claims file before you move. Hospitals have been required to publish standard charges since 2021. Separately, the Transparency in Coverage rules require most group health plans and insurers to publish machine-readable files with in-network negotiated rates, with the first files due July 1, 2022.16 These files are technical and can be difficult to use. KFF’s cited analysis documents challenges with hospital price files, not insurer rate files.17 Stacey noted that networks often contract with many of the same providers. My take: run the analysis, but do not expect a network change alone to fix your trend.

Direct contract where it counts. Evan pointed to direct or advanced primary care tied to value-based incentives, and Centers of Excellence for areas like orthopedics, cancer, and GI care. My take: direct contracting is an option, subject to plan terms, network adequacy, and administrative requirements. Start with services where your spend is highest and your data is clearest.

Steer and tier, including site of care. Evan said tiering should include where care happens, not just who provides it. Stacey cautioned that moving patients is not as simple as shifting interchangeable pieces, and she is right. We have learned how nuanced care plans and drug combinations can be, and why moving some patients is not appropriate. It takes clinical expertise to know who can safely move, when, and where. It also takes plan design. Give members a financial reason to choose the better path, so it feels like a benefit, not a penalty. The first message should be clear: this is the same drug and treatment plan, and a clinician has confirmed the proposed site is appropriate.

Bundle episodes of care. Evan described bundling as covering as many as 150 types of care episodes through a single-price structure. Stacey noted that bundles need both buyers and providers, and can address all three network problems by making price, quality, and what was charged more visible. My take: employers should ask for bundles where the price, quality measures, and episode scope are clear.

The broker’s role is changing

The idea from this episode I keep coming back to came from Stacey. She said a broker’s role is shifting from shopping for networks and stop-loss to coordinating the pieces. Evan agreed that data has to be actionable.2

I could not agree more. “This network has a bigger discount” is no longer a strategy. Our industry has a bad habit of turning operating problems into marketing categories. Executives do not need another label. They need an advisor who can explain, in writing, why their biggest claims went where they went and what alternatives were considered.

Questions to bring to your next renewal

  • What are we actually paying, not just what discount are we getting?
  • Who checks whether our largest claims matched our contracts?
  • Where are our high-cost infusions happening, and could the same drug be delivered for less?
  • How are those claims affecting our stop-loss renewal?
  • Does our plan design reward members for choosing the better option?

The three dragons are real. Employers can challenge all three with better data, clearer contracts, and active oversight.

My thanks to Stacey for asking the questions we should all be asking, and to Evan for a clear map of the problem. Listen to the episode, then review your claims.

Footnotes

1. Stacey Richter, host, “EP531: Slaying the Three-Headed Monster of Health Plan Networks, With Evan Anderson,” Relentless Health Value, September 2026, https://relentlesshealthvalue.com/episode/ep531-slaying-the-three-headed-monster-of-health-plan-networks-with-evan-anderson.

2. “Transcript for EP531 With Evan Anderson,” Relentless Health Value, September 2026, https://relentlesshealthvalue.com/blog/transcript-for-ep531-with-evan-anderson.

3. Katy Talento, “I Have a Dream… of a Post-Network World,” AllBetter, April 3, 2026, https://www.katytalento.com/p/i-have-a-dream-of-a-post-network.

4. Mark Cuban, LinkedIn post on health care reform priorities, including standardized carrier contracts by provider type, January 2026, https://www.linkedin.com/posts/mark-cuban-06a0755b_for-those-legislators-who-are-working-on-activity-7420638969467576320-A82E.

5. Stacey Richter, host, “EP530: A Wildly Underappreciated Point: Overpaying for Infusions Means Overpaying for Stop-Loss Coverage, With Jake Velie and Keith Hartman, RPh,” Relentless Health Value, September 2026, https://relentlesshealthvalue.com/episode/ep530-a-wildly-underappreciated-point-overpaying-for-infusions-means-overpaying-for-stop-loss-coverage-with-jake-velie-and-keith-hartman-rph.

6. Yang Wang, Mark Katz Meiselbach, John S. Cox, Gerard F. Anderson, and Ge Bai, “The Relationships Among Cash Prices, Negotiated Rates, And Chargemaster Prices For Shoppable Hospital Services,” Health Affairs 42, no. 4 (April 2023): 516–525, doi:10.1377/hlthaff.2022.00977, https://pubmed.ncbi.nlm.nih.gov/37011313/.

7. Stacey Richter, host, “EP480: Payment Integrity Meets Health System Boasts, Such as Our Rates Are 2x Medicare, With Kimberly Carleson,” Relentless Health Value, June 26, 2025, https://relentlesshealthvalue.com/episode/ep480-payment-integrity-meets-health-system-boasts-such-as-our-rates-are-2x-medicare-with-kimberly-carleson.

8. Stacey Richter, host, “EP521: How Revenue Cycle Management (RCM) Became an Over $200 Billion Healthcare Hot Potato, With Andrew Tsang,” Relentless Health Value, July 22, 2026, https://relentlesshealthvalue.com/episode/ep521-how-revenue-cycle-management-rcm-became-an-over-200-billion-healthcare-hot-potato-with-andrew-tsang.

9. U.S. Departments of Labor, Health and Human Services, and the Treasury, “FAQs About Affordable Care Act and Consolidated Appropriations Act, 2021 Implementation Part 57,” February 23, 2023, https://www.dol.gov/agencies/ebsa/about-ebsa/our-activities/resource-center/faqs/aca-part-57.

10. Stacey Richter, host, “EP531: Slaying the Three-Headed Monster of Health Plan Networks, With Evan Anderson,” Relentless Health Value, September 2026 (transcript discussion of Jim Jusko’s argument), https://relentlesshealthvalue.com/blog/transcript-for-ep531-with-evan-anderson.

11. Stacey Richter, host, “EP501: Speaking of Infusions, Do You Want to Pay $135 or Do You Want to Pay $13,560 for the Exact Same Drug? With Ivana Krajcinovic, PhD,” Relentless Health Value, February 26, 2026, https://relentlesshealthvalue.com/episode/ep501-speaking-of-infusions-do-you-want-to-pay-135-or-do-you-want-to-pay-13560-for-the-exact-same-drug-with-ivana-krajcinovic-phd.

12. Paul Fronstin and M. Christopher Roebuck, “Location, Location, Location: Spending Differences for Physician-Administered Outpatient Medications by Site-of-Treatment,” EBRI Issue Brief no. 666, Employee Benefit Research Institute, September 24, 2026, https://www.ebri.org/docs/default-source/pbriefs/ebri_ib_666_siteneutrtreatment-24sept26.pdf.

13. Daniel Cullen et al., “Infusion Therapy Patient Outcomes Are Similar at Reduced Costs in Alternative Sites of Care Compared with Hospital Outpatient Departments,” Journal of Managed Care & Specialty Pharmacy 32, no. 3 (March 2026): 312–322, https://pmc.ncbi.nlm.nih.gov/articles/PMC12948754/.

14. Medicare Payment Advisory Commission, “Aligning Fee-for-Service Payment Rates Across Ambulatory Settings,” Report to the Congress, Chapter 8, June 2023, https://www.medpac.gov/wp-content/uploads/2023/06/Jun23_Ch8_MedPAC_Report_To_Congress_SEC.pdf.

15. Sun Life U.S., “What Drives Multimillion-Dollar Medical Claims? Sun Life Report Shows Secondary Health Conditions, Hospital Stays and Specialty Drugs Among Key Factors,” news release, May 21, 2026, https://www.sunlife.com/en/newsroom/news-releases/announcement/what-drives-multimillion-dollar-medical-claims-sun-life-report-shows-secondary-health-conditions-hospital-stays-and-specialty-drugs-among-key-factors/124097/.

16. Centers for Medicare & Medicaid Services, “Use of Pricing Information Published under the Transparency in Coverage Final Rule,” https://www.cms.gov/priorities/healthplan-price-transparency/overview/use-pricing-information-published-under-transparency-coverage-final-rule.

17. Justin Lo, Gary Claxton, Emma Wager, Cynthia Cox, and Krutika Amin, “Ongoing Challenges with Hospital Price Transparency,” Peterson-KFF Health System Tracker, February 10, 2023, https://www.kff.org/health-costs/ongoing-challenges-with-hospital-price-transparency/.

Biosimilars Are Not Enough

By Jake Velie, CPT, Founder, Chairman & CEO, National Integrative Health

Biosimilars are getting a lot of attention right now. They should. They are changing the economics of the drug channel. Provider-administered biosimilars now account for an estimated 6% of the Big Three wholesalers’ drug distribution revenue, but 23% of their gross profit.1

But employers should not confuse more biosimilars with automatic savings.

That is not how this market works.

A lower-priced drug only helps if the plan is positioned to capture the savings. Too often, it is not. The problem is not just the drug. The problem is the path the drug takes through the system.

PBMs control formularies. TPAs see claims on the medical side. Stop-loss carriers absorb catastrophic exposure. Clinical and sourcing partners see savings opportunities the rest of the chain misses. If those groups are not aligned, savings leak out fast.

That is why the biosimilar conversation needs to get bigger.

Channel strategy already shapes what employers actually pay. The three largest PBMs manage roughly 80% of prescription drug volume, and each one operates its own private-label drug business.2 Their 2026 formularies exclude most marketed biosimilars and favor versions sold by their own affiliates. In some cases, cheaper biosimilars share formulary space with higher-priced affiliated versions.3

On paper, that can look like a win. The economics are not that simple. Market control, formulary placement, specialty pharmacy steering, and vertical integration all influence whether lower-cost therapies actually lower employer spend.4

Then there is the other issue employers keep running into: some of the highest-cost drugs do not show up where people expect them.

Everyone watches the pharmacy benefit. Far fewer people watch the medical benefit, where infusion and provider-administered drugs are billed. That is where visibility drops. It is also where price swings with site of care.

The data is clear. A 2026 study of more than 52,000 matched infusions found that hospital outpatient infusions cost about 42% more than the same therapies delivered in an office, home, or ambulatory infusion center, with similar patient outcomes.5 Earlier employer claims research found hospital outpatient prices for some infused specialty drugs running as much as 84% higher than in physician offices.6

Those costs do not stay small. Sun Life’s latest analysis of more than 70,000 high-dollar stop-loss claims found that million-dollar-plus claims rose 46% from 2022 to 2026, with injectable and specialty drugs among the key drivers.7

So yes, biosimilars matter. But the real question is bigger: can the employer see the whole claim, compare the real alternatives, and make the right decision across every channel?

That is where good partners matter.

A strong PBM matters. A strong TPA matters. A thoughtful stop-loss partner matters. A clinical cost-management partner matters. The plans that get the best results do not rely on one point solution. They build alignment across everyone touching pharmacy, medical claims, reimbursement, and catastrophic risk.

That is how employers move from theoretical savings to real savings.

The right question is simple: what is the lowest net cost way to deliver the right therapy to the right patient? If the PBM has the best answer, use it. If the better answer sits outside that channel, go get it. If the site of care is driving the excess cost, fix the site of care. If the claim is hiding in the medical benefit, bring it into the light before it becomes a stop-loss problem.

Biosimilars are part of the answer. They are not the whole answer.

The employers who win here will not be the ones chasing headlines. They will be the ones building a model that connects biosimilar strategy, medical benefit visibility, site-of-care discipline, and aligned incentives across PBMs, TPAs, stop-loss carriers, and clinical partners.

That is how lower prices turn into lower spend.

Sources

1. Bryce Platt, “The Spinoff: How Biosimilars Are Becoming Wholesalers’ Next Hit Show,” Drug Channels, September 22, 2026, https://www.drugchannels.net/2026/09/the-spinoff-how-biosimilars-are.html

2. Tyler Novotny and Bryce Platt, “The Private Label Biosimilar Paradox in Medicare Part D,” Drug Channels, September 1, 2026, https://www.drugchannels.net/2026/09/the-private-label-biosimilar-paradox-in.html

3. Adam J. Fein, “The Big Three PBMs’ 2026 Formulary Exclusions: MFP, Private Label Biosimilars, and Direct-to-Patient Threats for PBMs,” Drug Channels, January 22, 2026, https://www.drugchannels.net/2026/01/the-big-three-pbms-2026-formulary.html

4. See notes 2 and 3; and Adam J. Fein, “Drug Channels News Roundup, April 2026: PBM Specialty Pharmacy Steering, MLR Profit Shifting, Hospitals’ Fake Prices, and a Peek Behind the Scenes at DCI,” Drug Channels, April 28, 2026, https://www.drugchannels.net/2026/04/drug-channels-news-roundup-april-2026.html

5. Daniel Cullen et al., “Infusion Therapy Patient Outcomes Are Similar at Reduced Costs in Alternative Sites of Care Compared with Hospital Outpatient Departments: A Matched Cohort Analysis of Infusion Therapy Across Multiple Chronic Conditions,” Journal of Managed Care & Specialty Pharmacy 32, no. 3 (March 2026): 312–322, doi:10.18553/jmcp.2025.25264, https://pmc.ncbi.nlm.nih.gov/articles/PMC12948754/

6. Paul Fronstin and M. Christopher Roebuck, “Location, Location, Location: Cost Differences in Health Care Services by Site of Treatment — A Closer Look at Lab, Imaging, and Specialty Medications,” EBRI Issue Brief no. 525, Employee Benefit Research Institute, February 18, 2021, https://www.ebri.org/docs/default-source/pbriefs/ebri_ib_525_siteoftreatment-18feb21.pdf

7. Sun Life U.S., “What Drives Multimillion-Dollar Medical Claims? Sun Life Report Shows Secondary Health Conditions, Hospital Stays and Specialty Drugs Among Key Factors,” news release, May 21, 2026, https://www.sunlife.com/en/newsroom/news-releases/announcement/what-drives-multimillion-dollar-medical-claims-sun-life-report-shows-secondary-health-conditions-hospital-stays-and-specialty-drugs-among-key-factors/124097/

The Infusion Spend Problem Self-Funded Health Plans Can No Longer Ignore

By Jake Velie, Founder, Chairman & CEO, National Integrative Health

Most people around a self-funded health plan already know pharmacy spend matters. What many still miss is where some of the biggest drug costs actually land.

They do not always show up in the PBM report. A meaningful share of high-cost drug exposure sits inside the medical claim, especially in infused and provider-administered therapies. That is where plans can lose control quickly, and where too many employers still rely on passive default pathways instead of active management.¹ ²

That is why infusion is drawing more attention.

This is not just a broker conversation. It is a plan sponsor conversation, a TPA conversation, a stop-loss conversation, and a PBM conversation too.

Rachel Strauss made the point clearly during our fireside chat: transparency is how you start to follow the money. She is right. Until a broker, plan sponsor, TPA, or carrier can see where a drug was billed, how it was sourced, and what site of care was used, they are not truly managing the claim. They are reacting to it after the cost is already in the plan.

The real issue is not only the drug, it is the pathway

Too many people still approach infusion spend as if the drug itself is the only variable that matters. It is not.

The economics are shaped by at least four factors: the therapy selected, the place of service, the reimbursement structure, and the discipline of the people managing the claim. When those variables go unmanaged, high-cost cases tend to flow to the most expensive channel.³ ⁴

That is why two plans can cover the same therapy for the same condition and still end up with very different financial outcomes.

Chris McLellan underscored an important point in the discussion: many of these opportunities first appear in the authorization process. That is where high-cost therapies can be identified, reviewed, and evaluated before they become fully embedded in the plan’s paid claims experience. That is also where a plan can determine whether a lower-cost but clinically appropriate pathway exists, whether a biosimilar should be considered, or whether the drug should be moved out of a hospital outpatient department and into a lower-cost setting.

That front-end work matters. Once a claim is paid through the wrong pathway, the plan is often left cleaning up a cost it could have prevented.

The same drug can create a very different claim

One of the clearest takeaways from the fireside chat was also one of the simplest: the same drug can cost dramatically different amounts depending on how it is sourced, where it is administered, and how the contract is structured.

We have seen that firsthand.

In one case discussed during the fireside chat, the plan reduced cost by roughly $80,000 per administration of Ultomiris after changing the procurement path and contracting structure while keeping treatment in the same physician-office setting. As I said during the panel, it was the same medicine, in the same chair, in the same building, just a different contract.⁶

That is the kind of issue brokers, plan sponsors, TPAs, stop-loss carriers, and PBMs should all be trained to spot.

When an infused claim is treated as fixed simply because the therapy is medically necessary, the plan often misses the larger question. The right question is not only whether the treatment should happen. The right question is whether it is being delivered through the lowest reasonable net-cost path.¹ ² ⁴

The Ultomiris case makes the point

This is where complex cases separate real operators from everyone else.

Ultomiris is a REMS drug. That means this is not just a pricing exercise or a basic site-of-care conversation. It requires a team that can work through sourcing rules, REMS requirements, provider coordination, plan authority, and the right administration pathway without losing control of the case.⁷

Many competitors do not handle cases like that. They may talk about infusion savings in the abstract, but they are not built to operationalize a REMS-governed case inside a live health plan.

That is why this particular case matters. It showcases NIH’s ability to handle any complex case in a health plan, not just the easy ones. If a team can navigate a case like Ultomiris correctly, it tells you something important about its ability to manage the rest of the book as well.

Why pre-cert and prior auth matter so much

If brokers, plan sponsors, TPAs, stop-loss carriers, and PBMs want to know where real leverage begins, it begins at pre-cert and prior auth.

That is the linchpin.

A claim can be routed toward the hospital outpatient department, or it can be redirected toward a more disciplined pathway. The difference often comes down to whether someone is evaluating the case early enough, with enough clinical detail and enough contractual flexibility, to intervene.

That is why data matters so much.

Self-funded plans with full-detail claims data can do far more than fully insured groups looking at high-level summary reporting. If the people managing the plan can see diagnosis codes, CPT detail, drug identifiers, and place-of-service patterns, they can start asking the right questions. Which infused therapies are driving the largest paid amounts? How much of that spend is happening in hospital outpatient departments? Which cases are clinically appropriate for redirection? What did the contract allow, and what did it prevent?³ ⁴ ⁵

Without that level of visibility, employers are not managing trend. They are absorbing it.

This is bigger than one claim

It is easy to look at infusion management as a one-off savings exercise. That is too narrow.

The value is not just in reducing the cost of one treatment. The value is in changing the trajectory of the plan.

When a high-cost infused claim is managed correctly, it can affect the immediate paid amount, the next renewal cycle, and the stop-loss conversation that follows. Those savings do not just show up once. They stack.

That is why plan sponsors, brokers, TPAs, stop-loss carriers, and PBMs should view this work as strategic, not tactical.

Rachel made another point worth holding onto: this is not as simple as shopping PBM to PBM. If the underlying plan documents and vendor contracts do not give the employer flexibility, the employer may know there is a better option and still be blocked from using it. That is not a drug problem. That is a contract problem.

Everyone around the plan needs to read those contracts like they matter, because they do.

Member experience still determines whether the strategy works

Savings alone are not enough. If a plan is going to redirect infusion care, the member experience has to be handled well.

That means the process must feel coordinated, supportive, and clear. It cannot feel like something is being taken away from the patient.

Chris spoke to that directly. In the strongest cases, the member is supported by case managers, clinicians, provider-office coordination, pharmacy coordination, and a clear treatment plan. When that happens, the experience becomes smoother, not harder.

That has been our view as well. When done right, a site-of-care change should not create chaos. It should create confidence.

What the market should do now

Brokers do not need to become infusion operators. Neither do plan sponsors, TPAs, stop-loss carriers, or PBMs. They do need to get sharper at spotting where infused drug spend is hiding and who, if anyone, is actually managing it.

That starts with a few direct questions:

  • Where are the highest-cost infused claims landing today?
  • How many are being billed through hospital outpatient departments?
  • What authority exists at pre-cert and prior auth to redirect them?
  • What does the SPD or vendor contract allow?
  • Who is accountable for documenting why a high-cost claim followed the path it did?

Those are the questions that move the conversation forward.

Infusion spend is getting more attention for a reason. Employers are starting to realize that hospital-based drug administration is not just a clinical event. It is also a purchasing decision, a network decision, and a governance decision.

The organizations that understand that will walk into renewals with a stronger story, better questions, and more ways to protect plan dollars.

Footnotes

  1. Internal NIH case notes describe a broker with more than 70 self-funded groups seeking an infusion carve-out for a 10/1 renewing group after review of claims including Keytruda and other J and Q codes.
  2. NIH case notes describe a broker request for deeper analysis of site-of-care adjustments and Cyramza repricing.
  3. PSG, 2026 Pharmacy Benefit Manager Customer Satisfaction Report. Internal notes summarizing 2025 specialty trend findings: gross specialty spend grew 10.8%, cost per claim was nearly flat at 0.1%, and utilization grew 10.6%.
  4. Magellan Rx Management, Medical Pharmacy Trend Report: Site of Care Optimization. Research cited by Magellan indicates that shifting clinically appropriate infusions from hospital outpatient departments to lower-cost settings such as physician offices, ambulatory infusion centers, or home infusion can reduce administration costs by 40 to 60%.
  5. U.S. Department of Labor, Employee Benefits Security Administration. Used here to support the employer-accountability and documentation framework for pharmacy-related spend oversight.
  6. Fireside chat example describing a case in which approximately $80,000 per administration was removed by changing procurement and contracting structure while keeping treatment in the same physician-office setting.
  7. NIH internal operating policy routes infusion drugs through a site-of-care feasibility workflow that reviews manufacturer labeling, FDA / REMS requirements, applicable clinical guidance, and the appropriate administration setting. REMS products are sourced domestically.

The GLP-1 Market Has Changed, Now Plans Need a Strategy

By Jake Velie, CPT, Founder, Chairman & CEO, National Integrative Health

The GLP-1 market has already changed. The real question now is not whether these therapies will keep growing. They will. The question is whether plan sponsors have a real strategy for managing them.¹ ²

Too much of the conversation is still framed the wrong way. It gets reduced to a yes or no coverage debate, cover it or exclude it, as if that alone settles the issue. It does not.² ³

Coverage alone is not a strategy. Exclusion alone is not a strategy either.

A plan sponsor can decide to cover GLP-1s and still lose control if there are no clear clinical criteria, no channel discipline, no oversight on duration of therapy, and no process for managing net cost. A plan can also choose to exclude them and still end up with pressure from members, employers, appeals, and market demand that does not go away.¹ ²

That is where the market is now. GLP-1s have moved past being a niche benefit question. They are reshaping employer conversations around pharmacy trend, specialty management, clinical governance, and fiduciary oversight.¹ ²

This split is already showing up in the market. PSG reported that nearly all plans now cover GLP-1s for diabetes, but only 40% offer them for obesity, and 49% of plans that do not cover obesity GLP-1s say they would not do so at any price. That tells you this is no longer a fringe benefits question. It is an active plan-design and cost-governance decision.³

That means the next step for plan sponsors has to be execution.

The first piece is clinical criteria. If a plan is going to cover these therapies, it needs a disciplined framework around who qualifies, under what conditions, with what documentation, and with what expectations for continued therapy. That includes diagnosis standards, prior therapy requirements where appropriate, prescribing oversight, and ongoing review. Without that structure, utilization expands faster than governance.² ³

The second piece is channel management.

Not every high-cost therapy should move through the same pathway without scrutiny. Plan sponsors need to know where a GLP-1 claim is being filled, what support programs may exist, what manufacturer assistance or patient advocacy pathways are available, and whether anyone is actively managing the lowest legitimate net-cost route. Too often, plans look at the claim only after the spend is already on the books.¹

That is reactive. It is not strategy.

We are also seeing what stronger GLP-1 discipline can look like in real plan modeling. In a de-identified jumbo-group analysis built on a U.S.-sourced formulary, NIH modeled a fixed all-in GLP-1 rate of $521 per utilizing member per month, 36% below the incumbent carrier’s standard estimate and 57% below its risk-managed estimate. That translated to projected annual savings of $11.5 million to $25.8 million, depending on member take-up.⁴ ⁵

Just as important, tighter guardrails did not raise the unit cost in that modeling. BMI thresholds, prior authorization, step therapy, and lifestyle-program requirements could be layered on without changing the price per fill. Under the incumbent’s rebate-based model, tighter eligibility raised the unit cost by 50%.⁴ ⁵

The third piece is net-cost discipline. This is where a lot of employers still stop too early. They may get more visibility into pricing, but visibility by itself does not solve the problem. Seeing spend is not the same as controlling spend. A report can tell you what happened. It cannot prove the plan used the best available pathway.¹ ²

That matters because GLP-1 demand is not slowing down. As more employers face pressure from utilization, workforce interest, and broader market normalization, the plans that do well will not be the ones with the loudest position. They will be the ones with the clearest process.¹ ³

That process should answer a few simple questions.

1. Who qualifies for therapy?

2. What clinical criteria must be met?

3. What channel should be used?

4. What cost-support options have been evaluated?

5. Who is accountable for the net result to the plan?

If a plan sponsor cannot answer those five questions clearly, it does not have a GLP-1 strategy yet.

This is also where employers need to be careful about confusing vendor activity with accountability. PBMs, TPAs, brokers, consultants, and clinical vendors may all play a role. But someone has to own the full picture. Someone has to be responsible for making sure access, clinical integrity, and financial stewardship are working together.

That is the gap I see in this market.

The conversation is finally catching up to the size of the issue. That is a good thing. But the next move cannot be more debate without operational discipline. Plans do not need another round of abstract opinions on GLP-1s. They need criteria. They need process. They need channel control. They need net-cost management.¹ ² ³

In short, they need a strategy.

Footnotes

1. Managed Healthcare Executive. “Growth of GLP-1 Therapies Has Reshaped the Market.” PBMI 2026, as summarized in AHIP Solutions SmartBrief, Sep. 15, 2026: GLP-1 therapies accounted for almost half of prescription drug sales growth, the diabetes market reached $98 billion, and weight loss treatments grew 75% year over year to $55 billion.

2. PLANSPONSOR. “Navigating the Current Landscape of GLP-1 Coverage.” Sep. 11, 2026. PLANSPONSOR NewsDash summary noting that attorneys from McDermott Will & Schulte reviewed the costs, benefits, and risks employers should evaluate when deciding how their benefits address GLP-1 medications.

3. PSG 2026 Trends in Drug Benefit Design Report webinar notes shared internally on Jun. 25, 2026: nearly all plans now cover GLP-1s for diabetes, 40% offer GLP-1s for obesity, and 49% of plans that do not cover obesity GLP-1s would not do so at any price.

4. National Integrative Health, de-identified GLP-1 coverage cost analysis for a jumbo labor health and welfare fund, Aug. 2026: modeled fixed all-in GLP-1 pricing at $521 per utilizing member per month, compared with incumbent estimates of $800 standard and $1,200 risk-managed.

5. National Integrative Health. GLP-1 Program Case Study, de-identified illustrative summary, 2026: projected annual savings of $11.5 million to $25.8 million depending on member take-up, with the same pricing holding under added utilization-management guardrails.

The Era of Passive Health Plan Oversight Is Ending

By Jake Velie, CPT, Founder, Chairman & CEO, National Integrative Health

Employers are getting squeezed from every direction on healthcare costs. That part is not new. What is changing is how they are starting to respond.¹ ²

For years, many plan sponsors treated high-cost healthcare as something to review after the fact. They got the renewal. They looked at the trend. They asked a few questions. Then they assumed the vendor stack had it covered.

That approach is breaking down.

U.S. healthcare costs have reached $5.7 trillion, more than $15,000 per person per year. At the same time, nearly 60% of surveyed employers told Marsh they plan to make benefits changes next year to help control costs.¹ ² That is not a minor adjustment. It is a signal that employers know the old model is not holding.

The conversation is also becoming more explicit about fiduciary duty. Plan sponsors are being pushed to understand and implement CAA provisions, meet fiduciary responsibilities, and build stronger processes aligned with ERISA requirements.³ This is not just a cost conversation anymore. It is a governance conversation.

That matters because the real problem is not only price. It is fragmentation.

The PBM may manage one piece. The TPA may manage another. The broker may see the problem but not operate the fix. The employer is left trying to connect the dots after the spend is already on the books.

That is why more employers are looking for partners who do more than administer benefits. They are looking for people who can help them act like fiduciaries.

High-cost claims make that need impossible to ignore. One outside analysis put it plainly: 80% of healthcare costs are driven by 20% of claimants, and 50% of healthcare costs are driven by 5% of claimants.⁴ When that much risk is concentrated in that few cases, passive oversight is not a strategy.

Pharmacy pressure only adds to it. Specialty medications now comprise nearly 80% of all new drug launches, and nearly half of those launches carry price tags above $150,000.⁵ Employers do not need more summaries telling them costs are rising. They need someone who can challenge the pathway before a bad default becomes a paid claim.

That is the shift happening now. Employers are asking harder questions. Where is spend concentrating? Which claims are being actively challenged? What alternatives were reviewed? Who owns the decision? How do we prove the plan bought well, not just processed correctly?

Those are fiduciary questions. And once employers start asking them, they usually realize generic oversight is not enough.

This is why specialized partners are getting more attention. Not because employers want another logo in the stack. They do not. They want control. They want accountability. They want a party that can step into the space between administration and outcome and actually manage the problem.

That does not require self-promotion to explain. It is simply where the market is headed. When costs rise, risk concentrates, and compliance expectations get tighter, employers move toward expertise that is operational, clinical, financial, and accountable at the same time.

The era of passive health plan oversight is ending.

And for employers who are serious about cost, that is a good thing.

Footnotes

1. Moving to Value Alliance, “Enough with the Blank Checks,” Sep. 15, 2026. Summary states that U.S. healthcare costs have reached $5.7 trillion, more than $15,000 per person per year, and frames a 12 to 24 month roadmap from passive payer to active fiduciary. Link shared by user: https://www.movingtovalue.org/enough-with-the-blank-checks?utm_campaign=7ebc36f3-b142-46b4-acf7-6228b99dc19c&utm_source=so&utm_medium=mail&cid=322adc3d-c936-40c5-815b-713c3ca416dd

2. PLANSPONSOR NewsDash, “Employers Gear Up for Biggest Healthcare Cost Spike in 20 Years,” Sep. 8, 2026. Summary notes that nearly 60% of surveyed employers told Marsh they planned to make benefits changes next year to help control costs.

3. PLANSPONSOR, “Your Health Benefit Fiduciary Roadmap Starts Here!,” Mar. 25, 2026. Invitation copy states the series would help plan sponsors and advisers understand and implement CAA provisions, confidently meet fiduciary responsibilities, and build robust processes aligned with ERISA requirements.

4. AHealthcareZ, Eric Bricker, MD, “#1 Cause of High Healthcare Costs is…,” Oct. 28, 2025. Summary states that 80% of healthcare costs are driven by 20% of claimants and 50% of healthcare costs are driven by 5% of claimants.

5. RxBenefits Team, “Take Control of Specialty Drug Costs,” Aug. 24, 2026. Summary states that specialty medications comprise nearly 80% of all new drug launches and nearly half of them carry price tags exceeding $150,000.

Why Brokers Are Asking for Infusion Carve-Outs Now?

By Jake Velie, Chairman & CEO, National Integrative Health

When brokers start raising infusion carve-outs in renewal conversations, it is a sign that the old approach to medical-benefit drug spend is under pressure.

This is not a labeling exercise. It is about cost, accountability, and control.

In one recent NIH case, a broker managing over 70 self-funded groups asked whether an infusion carve-out could be put in place for a 10/1 renewal after reviewing claims that included Keytruda and other J and Q codes.¹ (Source note: Internal NIH case notes.) In another July case, a broker requested a deeper repricing analysis focused on site-of-care adjustments and Cyramza.² (Source note: NIH case notes on site-of-care repricing.) Those cases matter, not because two anecdotes prove a trend, but because they reflect where sophisticated intermediaries are starting to focus.

They are looking harder at provider-administered drugs billed through the medical benefit. They are asking what the plan actually paid. They are questioning whether the hospital outpatient department was the right setting. And they are recognizing that a standard renewal conversation does not answer those questions well enough.

What an infusion carve-out means in practice

An infusion carve-out is not a solution by itself, and it is not automatically the right answer.

At a practical level, it usually means separating some portion of infused and injected drug management from the default medical-claim workflow so the plan can evaluate a different mix of site of care, sourcing, prior authorization, clinical review, and network strategy. The point is not the carve-out itself. The point is to stop treating every infused claim as if its current pathway must be accepted.

That distinction matters.

Too many employers still approach infusions as though the only variable is the drug. In reality, the economics are shaped by at least four moving parts: the therapy selected, the place of service, the reimbursement structure, and the discipline of the people managing the claim. When those four variables go unmanaged, high-cost cases consistently flow to the most expensive channel.

Why brokers are raising this now

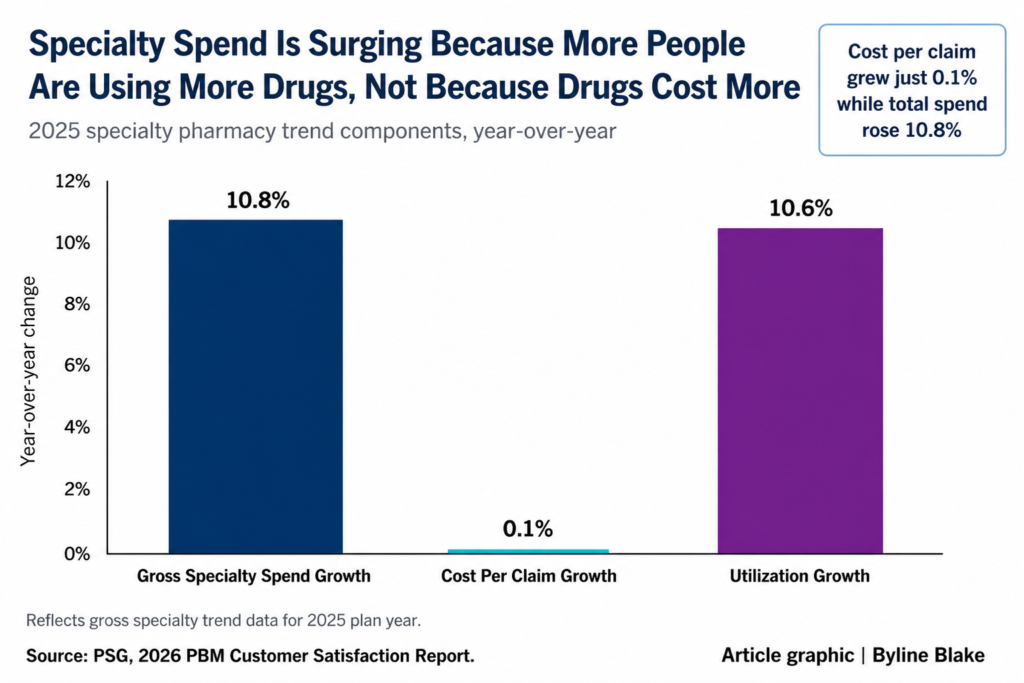
The broader specialty market is already telling employers that high-cost drug management cannot be treated as a rebate exercise. In PSG’s latest specialty trend discussion, gross specialty spend grew 10.8 percent in 2025 while cost per claim was nearly flat at 0.1 percent. Utilization grew 10.6 percent.³ (Source note: PSG specialty trend findings.) More members are using more high-cost therapies, across more conditions, for longer periods of time.

Figure 1: Specialty Spend Is Surging Because More People Are Using More Drugs, Not Because Drugs Cost More

That utilization dynamic is especially important in the infusion setting.

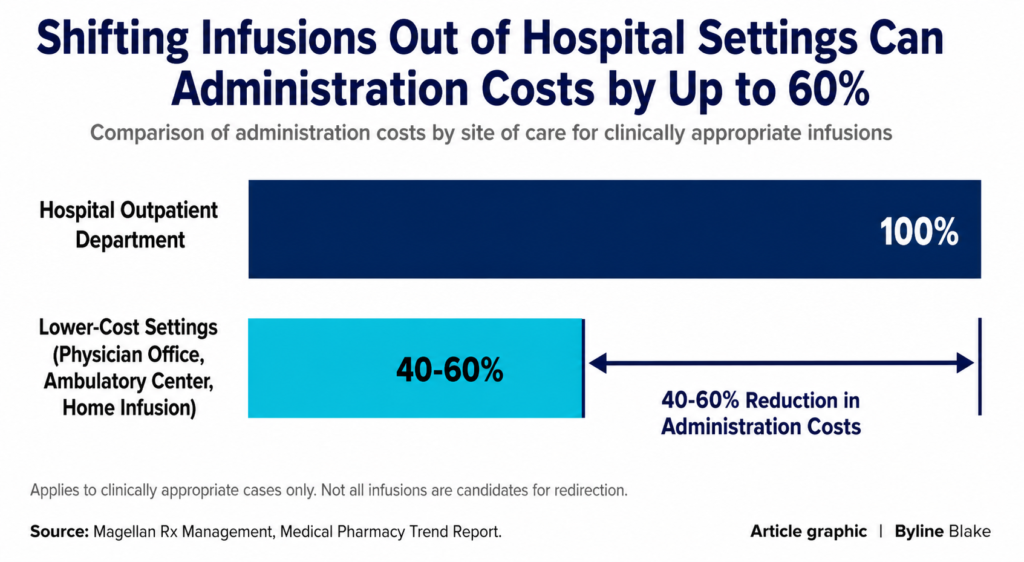
Once more high-cost therapies move through the medical benefit, the site of care starts to matter significantly. Magellan Rx Management has cited research showing that shifting infusions from hospital outpatient departments to clinically appropriate lower-cost settings such as physician offices, ambulatory infusion centers, or home infusion can reduce administration costs by 40 to 60 percent.⁴ (Source note: Magellan site-of-care optimization research.) That does not mean every infusion belongs outside the hospital. It does mean every routine case deserves scrutiny.

Figure 2: Shifting Infusions Out of Hospital Settings Can Cut Administration Costs by Up to 60%

That is why brokers are asking harder questions. They are seeing the same thing employers are seeing in their claims experience: infused drug spend is not something you can review once a year and set aside.

The problem is not just price. It is process.

The structural problem for many plans is that they do not have a clean answer to a simple question: who is responsible for proving that a high-cost infused claim was routed through the lowest reasonable net-cost path?

The PBM may not own it if the drug is billed through the medical benefit. The TPA may process the claim correctly without knowing to challenge the site. The broker may spot the problem without being aware how to operate the fix. The hospital has no reason to volunteer a lower-cost setting if the current one pays well.

That leaves the plan sponsor holding the financial risk and, increasingly, the governance burden. As the U.S. Department of Labor and Employee Benefits Security Administration continue to press for greater health-plan transparency and accountability, employers should assume they need a clearer record of how high-cost pharmacy-related claims are being evaluated and managed.⁵ (Source note: DOL and EBSA guidance on oversight and accountability.)

This is why infusion carve-out conversations keep reaching the renewal table. They are often less about replacing a vendor and more about creating a process that does not depend on passive default behavior.

What plan sponsors should evaluate before making a decision

A sound infusion strategy starts with diligence, not positioning.

Before a plan sponsor embraces or rejects a carve-out, there are several practical questions worth answering:

  1. Which infused and injected therapies are driving the highest paid amounts today?
  2. How much of that spend is occurring in hospital outpatient departments versus lower-cost alternative settings?
  3. For the largest claims, does the plan know the true net paid amount after all credits, refunds, and adjustments?
  4. Which cases are clinically appropriate for redirection, and which are not?
  5. Is the plan evaluating biosimilars, site-of-care changes, and other cost levers together, or one at a time?
  6. Who is documenting the rationale for the path chosen on the largest claims?

That is the conversation self-funded employers should be having.

A plan does not need an ideological view of carve-outs. It needs a disciplined view of whether the current structure is producing defensible outcomes.

What gets lost when this becomes a vendor conversation

The industry tends to turn real operating problems into marketing categories.

The important issue is not whether an employer adopts a vendor’s preferred label. The important issue is whether the employer can demonstrate that it understands where infused drug spend is landing, why it is landing there, and what alternatives were considered.

If a carve-out helps create that discipline, it is worth considering. If the same discipline can be achieved through other means, that is equally valid. But inaction is no longer a defensible position.

When high-cost infused claims continue to flow into expensive settings without a documented challenge process, the plan is not managing the trend. It is absorbing it.

What employers should do next

Do not wait until the next renewal to get clarity on infused drug spend.

Pull the high-cost claims. Identify the sites of care. Reconcile the true net paid amounts. Review which therapies could have been managed differently. Make sure someone can explain, in writing, why the current pathway was used on the largest cases.

Infusion carve-outs are getting attention because employers are finally confronting a simple reality: hospital-based drug administration is not just a clinical event. It is a purchasing decision, a network decision, and a governance decision.

The plans that take that seriously will be in a much better position than those still treating infused drug spend as an unavoidable cost of doing business.

Jake Velie is Chairman & CEO of National Integrative Health, a managed services organization headquartered in West Des Moines, Iowa, focused on prescription drug cost optimization for self-funded employer health plans.

Footnotes

  1. Internal NIH case notes describe a broker with 70 groups seeking an infusion carve-out for a 10/1 renewing group after review of claims including Keytruda and other J/Q codes.12
  2. NIH case notes describe a broker request for deeper analysis of site-of-care adjustments and Cyramza repricing.
  3. PSG, 2026 Pharmacy Benefit Manager Customer Satisfaction Report. Internal notes summarizing 2025 specialty trend findings: gross specialty spend grew 10.8%, cost per claim was nearly flat at 0.1%, and utilization grew 10.6%.
  4. Magellan Rx Management, Medical Pharmacy Trend Report: Site of Care Optimization. Shifting clinically appropriate infusions from hospital outpatient departments to lower-cost settings can reduce administration costs by 40 to 60 percent.
  5. U.S. Department of Labor, Employee Benefits Security Administration. Used here to support the employer-accountability and documentation framework for pharmacy-related spend oversight.

PBM PUGILISM – With the Big Three Pharmacy Benefit Managers Facing greater scrutiny, more independent players are jockeying for position

Written by Bruce Shutan

David vs. Goliath battle continues to intensify across the pharmacy benefit management landscape as self-insured employers struggle with reining in their Rx spend.

In one corner lie the so-called Big Three PBMs, which are vertically integrated with the nation’s largest health insurance companies and control about 80% of U.S. prescription drug claims. They include Express Scripts, which is owned by Cigna, CVS Caremark, which owns Aetna, and OptumRx, which is owned by the same parent company as UnitedHealthcare.

At the other end of the ring are nearly 100 independent PBMs scrambling for the remaining slice of market share. Many claim their model is “transparent,” while a handful go out on a limb to describe their offering as “fiduciary.” But industry experts say semantics can be misleading.

Self-insured group health plans appear to be giving the proverbial Davids of this industry a closer look. Consider, for example, that as many as 92% of 300 benefits decision-makers surveyed by the Penta Group for Evernorth believe a model that passes savings directly to members would improve transparency. Moreover, 90% said a PBM model without rebates would make it easier for employees to afford their medications and improve benefits satisfaction.

Higher Expectations

Jeff Malone

Whereas transparency was a differentiator nearly a decade ago in the PBM space, it’s now a minimum expectation, opines Jeff Malone, Co-Founder, President, and CEO of RxPreferred. He says the conversation has shifted to whether transparency is complete, auditable, and aligned, while the future will be backed by aligned incentives and real-time data.

“Independent PBMs are gaining traction, especially among employers and health systems seeking greater flexibility and alignment,” Malone observes, noting how employers are now looking beyond size and perceived discounts. “They’re asking tougher questions about pricing, rebates, data ownership and conflicts created by vertical integration.”

A mass migration among small and midsize businesses from fully insured health plans to level-funding and self-funding has changed the rules of engagement with PBMs in recent years. “We’re seeing a big shift of market share increasing into that transparent PBM tranche in the market simply because of affordability,” says Jake Velie, Chairman and CEO of National Integrative Health.

Another huge driver is the federal government ramping up regulatory scrutiny of PBM practices, with Acting Labor Secretary Keith Sonderling making the drafting of new PBM transparency regulations a top priority.

Several states have also tried to block PBM ownership of pharmacies, concerned about conflicts of interest that may arise with such enormous scale. Arkansas is the only state that has enacted a law to do just that (in 2025), while proposals are pending in Tennessee and Arizona and under consideration in Indiana and Connecticut. Iowa also is considering aggressive PBM reforms.

A Curtain Of Complexity

Renzo Luzzatti

It’s easy to see why this is happening. The fact is that PBMs have operated behind a curtain of complexity for far too long, earning billions each year from spread pricing, rebate retention and opaque formulary steering in contracts with health plan sponsors, Velie argues.

US-Rx Care President Renzo Luzzatti doesn’t see much clinical diligence or rigor across the transparent PBM industry in part because many of those owners haven’t ever done a prior authorization. “You got folks that were tired of pharmacy margins, and so they started a PBM,” he opines.

In light of these headwinds, his firm fields peer-to-peer calls with doctors on a regular basis, noting that the quickest way to resolve a disagreement is to simply pick up the phone and have a conversation with a clinician. In one case, he recalls how a doctor eventually admitted to prescribing a 40% higher growth hormone dosage for a patient that needed to be corrected. It saved the plan $33,000. “This stuff happens every day,” he reports.

A pioneer in the independent PBM space, Luzzatti is aware of only a handful of organizations in the marketplace that – like his firm and Velie’s – actually describe themselves as a “fiduciary” PBM or pharmacy program. To do that, it means pledging that there will be no conflict of interest, such as accepting rebate money; they will look out solely for the best interest of the plan and its participants; and all utilization and financial information is in full view.

“We cite the ERISA regs, and it means that we’re held to the same legal standard as our self-insured employer clients are as fiduciaries of their own plan,” he says.

That contrasts with common language in PBM contracts that explicitly state that they’re not a fiduciary and not obligated to act in a fiduciary manner, he adds. Some will even allow for contracts to be canceled if a state requires PBMs to be a fiduciary.

In addition, he says there are PBMs that call themselves transparent while also claiming they’re not obligated to act in a fiduciary manner. Most times, the inference is that they charge an admin fee and don’t do spread pricing. In that regard, Luzzatti explains that the word transparency is nebulous. “It’s not a legal term. You can’t take them to court over that. It’s whatever they say it is,” he says.

A PBM may position certain formulary drugs in tier one and tier two to access greater rebates from the manufacturer, and hence usually pocket them, Velie observes. “You’re keeping certain brand drugs in a preferred tier when you should be putting a biologic there,” he says.

The only industry players that actually meet the definition of a fiduciary PBM are those that are willing to do the reporting necessary for the fiduciary filing for the plan sponsor and hand them over to comply with their duties under the Affordable Care Act and Consolidated Appropriations Act of 2021, Velie notes.

An Ability To Access Data

Jake Velie

True price transparency lies in how PBMs get paid. “If we look at the PBMs that we like to work with, there’s no funny business in the contracts,” he explains. “They’re not trying to hide behind intellectual property contingencies in the contract. They’re showing you what the pricing is. Their fees are flat.”

His company works with some PBMs that charge a per-script fee, while others charge an admin fee.

Neither of those natural-flow models is easy to manipulate. He says there’s very little that a PBM can hide if the data is available. National Integrative Health deploys a multi-lever approach to achieve the lowest net cost on every claim for every member. It includes 340B pricing, biosimilars, 503B manufacturer direct contracting, variable copay programs, clinical interventions and clinical trial program access.

Many of the transparent and fiduciary PBMs are operating on Big Three chassis that they’re white labeling, Velie says. What’s different is their business and contract practice, as well as a commitment to data transparency for the end client. Their relatively slow adoption can be traced to the snail’s pace of imposing regulatory changes on the healthcare industry when lobbyists still hold considerable sway over lawmakers, he adds.

While jumbo employers can afford to stay with the Big Three, he notes that they’ve already been forcing them to improve practices because they have the leverage to do just that. Significant change is already afoot. For example, CVS Caremark recently agreed to allow clients to opt out of standard rebate-based payment designs and pass discounts directly through to consumers as part of a settlement with the Federal Trade Commission. Despite that move and any others that might follow, Velie believes the Big Three will still give careful thought to how they’re going to recover that lost revenue in other areas.

Underwriting Decrements

Scott Byrne

From a high-level strategic standpoint, the PBM serves as a linchpin to get underwriting consideration for plan design and execution on high-cost drugs, according to Velie.

“We are constantly working with stop-loss carriers in underwriting and actuarial practices because we can predict our outcomes when we have the right plan design,” he reports. “So, when we give them our analysis during the underwriting process, it is guaranteed to work, and we are seeing normally up to 10% reductions in stop-loss renewals because we have the right formula and we cannot execute on the right formula without the right PBM partner.”

Blackwell Captive Solutions President Scott Byrne notes that as recently as three to five years ago, “most stop-loss carriers were not offering decrements for PBMs. It just wasn’t being factored into their manual rate whatsoever. They would factor in network and TPA, but PBMs surprisingly were left out of the mix.”

Since that time, he says prescription drug costs swelled from roughly 20% to 25% of an employer’s annual health plan spend to more than 50%. Therefore, he believes this bigger piece of the pie deserves to be addressed and accounted for in a health plan’s pricing.

Given all that’s at stake, pharmacy benefits are becoming a year-round risk management function instead of an annual renewal discussion, according to Malone. He says claim-level visibility allows employers to identify high-cost trends early, manage specialty drugs and GLP-1s proactively and coordinate pharmacy strategy with the broader health plan.

One health system client of his was able to reduce pharmacy costs by 38% through a combination of transparent PBM administration, active utilization management and customized pharmacy strategies that leveraged its own pharmacy resources.

Eyeing Efficacy

Katherine Shanahan

While the cost of prescription drugs is top of mind, so is the impact on clinical outcomes. Pressure is mounting on self-insured employers to determine whether drugs on their formulary are actually benefiting health plan members relative to other scripts in the face of rising medical and pharmacy costs, observes Katherine Shanahan, Director of Pharmacy Consulting for Merative. To put it another way, is there a meaningful enough return on investment?

The use of GLP-1s for weight loss has spotlighted this concern. She says there’s such a high rebate percentage for these drugs that without price transparency, it’s difficult to determine whether there are downstream health improvements and savings from patients no longer experiencing flare-ups.

While huge biometric improvements have been seen with GLP-1s, she notes that there’s still a lot of exploration with regard to stepping down a patient over time and realizing that longevity requires a different cost model.

A Restless Market

While some health plan participants are more comfortable having a household name on their ID card, Byrne believes smaller independent PBMs are achieving the most progress relative to the Big Three when it comes to transparency.

He uses a construction analogy to describe the captive-PBM relationship, noting that the captive serves as the general contractor that builds a meaningful risk-management strategy and hires a PBM as one of several subcontractors. Choosing the right PBM is critical. “We want to bring best-in-class point solutions to our members because ultimately we need to be good stewards of their money,” he says.

As many as 30% of the employer population is out to bid now on a PBM in the course of a typical year, Luzzatti reports, noting that frustration is mounting upstream to jumbo employers and predicting that most self-insured clients will have made a change in three years.

“Their concern from a legal standpoint is that they might be the next target like Johnson & Johnson, Wells Fargo and JPMorgan Chase. Nobody wants that,” he says.

Velie predicts that there will be a meaningful shift in the market away from the Big Three given these high-profile lawsuits alleging that employers are overcharging for prescription drugs, and as a result, breaching their fiduciary responsibility under ERISA to act in the best interest of plan participants.

“I think they can only survive so much bad publicity,” he says of the Big Three, “and now that these fiduciary and transparent PBMs are getting up to the point where they’re scalable, they can handle larger populations and serve their clients well. I think over the next five years, that segment of the PBM market will see more growth than they’ve seen in the last 15.”

Historically, Shanahan points to constraints in the request-for-proposal process that have eliminated smaller or boutique PBMs from contention. However, she sees more midsize health plans having them at least fill out the remainder of the RFP and change some of the metrics they’re looking at even though they didn’t rank highest.

Adds Malone: “Transparency tells an employer what happened. Alignment determines why it happened and whether the PBM had an incentive to deliver the best result.”

Bruce Shutan is a Portland, Oregon-based freelance writer who has closely covered the employee benefits industry for nearly 40 years.

From The Self-Insurer, September 2026 Edition